



Key Takeaways
- Clinicians already adopted it. 81% of physicians used AI professionally in 2026, more than double the 2023 rate, across roughly 1,700 respondents in the AMA’s 2026 Physician Survey on Augmented Intelligence.
- The money is in administration. Around 10% of US national healthcare expenditure, roughly $400 billion, relates to administrative complexity. CAQH tracks $89 billion of that in administrative transactions, of which $18.3 billion is recoverable simply by moving to fully electronic processing.
- The documented wins are documentation. The top physician uses are summarising research (39%), drafting discharge instructions and care plans (30%), documenting billing codes and charts (28%) and generating chart summaries (28%). Assistive diagnosis sits last at 17%.
- Algorithm transparency is now a certification requirement. The ONC HTI-1 final rule requires certified health IT to disclose 31 source attributes for every Predictive decision support intervention, and to maintain risk analysis, risk mitigation and governance practices.
- Budget realistically. SoluLab’s healthcare AI solutions development starts at $18,000 for a non-enterprise-grade app to $60,000+ for a full enterprise platform, with healthcare in the top industry band alongside banking and insurance.
- SoluLab’s clinical platform is measured, not asserted. The GenAI in MedTech build cut diagnostic errors by 35%, sped clinical decision-making by 40% and cut documentation drafting time by 60%, on a HIPAA-compliant architecture using HL7 and FHIR.
AI in healthcare is the use of machine learning and generative AI across three distinct areas: clinical decision support, administrative work such as documentation, coding and prior authorisation, and operational work such as scheduling, capacity and revenue cycle. The administrative and operational applications carry the lowest regulatory risk and the fastest payback, which is why most providers start there. This guide covers the AI solutions in healthcare that pay back first, what compliance demands of them, and what healthcare AI solutions development realistically costs.
Increasing patient numbers, clinician burnout, rising costs of operation, and rising chronic diseases are pushing hospitals to their limits. Simultaneously, huge volumes of medical information are not fully used, which suppresses diagnosis and restricts preventive care.
The point of concern is that conventional healthcare models are unable to sustain such a rate of demand. Efficiencies in administration, workforce deficiencies, and delayed treatments are increasing.
However, artificial Intelligence can serve as a viable way out. AI is changing the way healthcare is delivered with predictive diagnostics and customized treatment plans, automated documentation, and real-time patient monitoring.

What is AI in healthcare?
AI in healthcare is the application of machine learning, natural language processing and generative AI to clinical, administrative and operational healthcare work, so that documentation, coding, triage, scheduling and decision support can be done faster and more consistently than by manual effort alone.
The term covers three categories of AI solutions for healthcare that have almost nothing in common from a risk or build perspective. Conflating them is why healthcare AI budgets get set badly.
Clinical AI touches diagnosis, treatment or patient management. An imaging model flagging a nodule, a sepsis early-warning score, a differential diagnosis generator. This category may be a regulated medical device, it carries patient-safety liability, and it demands clinical validation. It is also the category the press writes about, which skews executive expectations.
Administrative AI handles the paperwork around care: clinical documentation, coding, prior authorisation, claims, correspondence, referral letters, chart summarisation. No patient-safety decision is being made by the machine, the clinician still signs. This is where most of the measurable financial return sits in 2026.
Operational AI runs the organisation: scheduling and no-show prediction, theatre and bed capacity, staffing rosters, supply forecasting, revenue cycle. Same low clinical risk, and often the fastest payback of the three because the baseline inefficiency is large and easy to measure.
A Predictive decision support intervention, under the ONC HTI-1 rule, is technology supporting decision-making based on algorithms or models that derive relationships from training data and produce a prediction, classification, recommendation, evaluation or analysis. If your tool does that inside certified health IT, the transparency rules below apply to it.
A useful rule of thumb when prioritising healthcare AI solutions: if a wrong output harms a patient, treat it as clinical and budget for validation. If a wrong output costs money or time, treat it as administrative and ship it sooner.
Where does AI actually save money in healthcare today?
The clearest financial case for AI in healthcare is administrative, not clinical. Past analyses put administrative complexity at roughly 10% of US national healthcare expenditure, about $400 billion. The 2023 CAQH Index found $89 billion of that is spent conducting the administrative transactions it tracks, and that the industry could save $18.3 billion by moving the remaining manual and partially electronic transactions to fully electronic processing.
Two things in that data deserve attention.
First, the industry has already proved the mechanism works. CAQH reports that medical and dental providers avoid $193 billion annually through the automation already in place. The argument is not whether automation pays. It is that a large, specific, measured remainder is still manual.
Second, CAQH identified staffing churn as driving more than 75% of the rise in total administrative spend, because less experienced staff take longer to complete the same tasks. That is precisely the problem well-built artificial intelligence healthcare solutions address. They do not get tired, they do not leave, and they do not need to relearn the prior authorisation rules every time the team turns over.
What are the practical AI use cases in healthcare operations?
Eight AI in healthcare use cases account for most of the deployed value in provider organisations today. If you are evaluating AI for healthcare solutions, this is the shortlist to start from. They are ordered here by how quickly they tend to pay back, not by how impressive they sound.
1. Ambient clinical documentation. The system listens to the encounter and drafts the note, which the clinician edits and signs. This is the single most adopted healthcare AI application right now because the burden it removes is enormous and the failure mode is mild, a clinician correcting a draft rather than a patient being harmed.
2. Chart summarisation. Before an appointment, the system condenses a multi-year record into a structured summary: active problems, recent changes, medications, outstanding results. Specialists reviewing unfamiliar patients benefit most. 28% of physicians in the AMA survey already generate chart summaries this way.
3. Medical coding support. The model proposes codes from the documentation and flags where the note does not support the level billed. Treat the output as a suggestion to a certified coder, never as an autonomous billing decision, because the compliance exposure of getting that wrong is serious.
4. Prior authorisation assembly. The system reads the payer’s criteria, pulls the supporting evidence out of the record, and assembles the submission packet. This is the highest-frustration administrative task in most provider organisations and one of the better-defined automation targets.
5. Denial management and appeals. Denials get classified by root cause, and the system drafts the appeal with the relevant clinical evidence attached. The valuable output here is the pattern analysis, which tells you which upstream documentation gap is generating the denials in the first place.
6. Patient communication drafting. Portal messages get a drafted reply the clinician reviews before sending. 19% of physicians already do this. The governing rule is that a clinician sends, always.
7. Scheduling and no-show prediction. Models predict which appointments will be missed and drive overbooking or outreach accordingly. Unglamorous, quick to implement, and measurable within one quarter.
8. Referral and correspondence automation. Inbound referrals get read, triaged and routed with the clinical details extracted. Outbound letters get drafted. Referral leakage is usually a data problem before it is a relationship problem.
Notice what is not on this list: autonomous diagnosis. That is deliberate. The AMA data makes the same point from the clinician side, where assistive diagnosis is the least common use at 17%, well behind documentation and summarisation.
Current State of AI in Healthcare
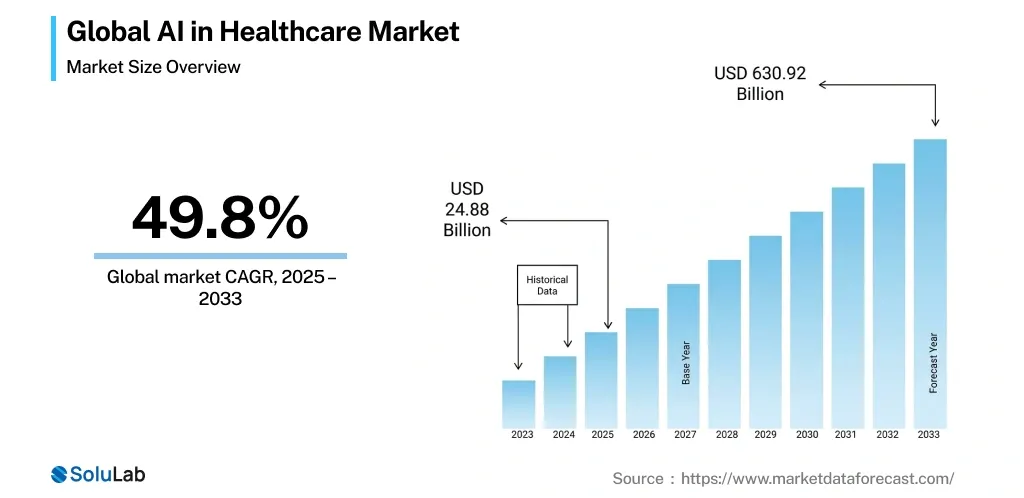
Artificial intelligence is no longer experimental in healthcare. It is also working towards diagnostics, drug research, hospital operations, and patient engagement, reinventing care delivery globally. The global AI in healthcare market is expected to reach 630.92 billion by 2033.
- Artificial intelligence in Diagnostics: Computer algorithms can now help radiologists locate cancers, fractures, and neurological conditions more quickly and with higher precision. Recent articles in Nature Medicine demonstrate that AI systems perform on par with, or even outperform, specialists in detecting breast cancer, thereby improving the overall rate of early cancer diagnosis.
- AI-Powered Drug Discovery: AI reduces drug discovery timelines by analyzing large biological datasets and screening potential compounds. According to McKinsey, AI has the potential to reduce the time needed to discover new drugs in the early stages by up to 40 percent and enable the pharmaceutical industry to lower the cost of R&D and shorten clinical trial durations.
- Clinical Decision Support Systems: Clinical decision support tools are AI-based technologies that analyze a patient’s medical history, labs, and medical literature to help physicians during treatment planning. Deloitte states that hospitals with developed analytics and AI-driven systems of decision-making can document improvements in the quality of care and operational efficiency.
- Virtual Health Assistants and AI Chatbots: Chatbots are used in healthcare and can help patients book appointments, identify symptoms, and answer questions 24/7. Juniper Research posits that healthcare chatbots can save the sector millions of dollars annually by reducing administrative staff and improving patient response times.
- Automation of Hospital Workflows: Hospital billing, documentation, scheduling, and supply chain management are automated using AI. Accenture research suggests that the US healthcare economy could save up to 150 billion US dollars annually through AI-based workflow automation, reducing operational waste.

Key Drivers Accelerating AI Adoption in Healthcare
The global healthcare sector is quickly embracing artificial intelligence as financial constraints, data explosion, patient demands, and the emergence of digital care frameworks reform the way healthcare facilities deliver efficient, patient-centered, and scalable healthcare services.
- Increasing Healthcare Costs: Global healthcare expenditure amounted to about 9.8 trillion, just under 10 percent of global GDP. Automation, predictive analytics, and workflow optimization are among the ways AI can lower administrative expenses, which account for up to 2530 percent of hospital expenses.
- Expansion of Healthcare Data: Healthcare produces some 30 percent of all data on the planet and is increasing by 36 percent per year. AI can help providers work effectively with medical imaging, electronic health records, and genomic data, transforming complex data into actionable clinical insights.
- Need for Personalized Medicine: Precision medicine is booming at a very high rate, and the market is expected to reach over 175 billion across the world by 2030. AI examines genetic, lifestyle, and clinical data to prescribe individualized treatment to improve outcomes and minimize unnecessary interventions.
- Growth of Telemedicine: The use of Telehealth had reached approximately 38 times that recorded before the pandemic. AI can improve the accessibility of virtual consultations through symptom triage, automated documentation, and real-time monitoring, reducing providers’ workload.
Why Healthcare Organizations Partner with AI Development Companies
Healthcare organizations partner with AI development companies to overcome technical complexity, accelerate innovation, and deploy scalable, compliant solutions that improve patient outcomes while reducing operational costs and inefficiencies.
- Access to Specialized AI Expertise: AI development companies bring deep expertise in machine learning, data engineering, and healthcare compliance, enabling organizations to build accurate, reliable, and production-ready AI solutions without hiring large in-house teams.
- Faster Time-to-Market: With proven frameworks, tools, and pre-built models, AI partners accelerate development cycles, helping healthcare providers deploy solutions quickly and start realizing value without long implementation delays.
- Integration with Existing Systems: AI development companies ensure smooth integration with EHR systems, hospital software, and legacy infrastructure, minimizing disruption while enhancing workflows and maintaining data consistency across platforms.
- Regulatory Compliance and Security: Experienced AI vendors understand healthcare regulations like HIPAA and GDPR, ensuring secure data handling, audit trails, and compliance-ready systems that reduce legal risks and protect patient information.
- Cost Optimization and Scalability: Partnering with AI companies helps reduce development and operational costs by leveraging scalable cloud infrastructure, reusable components, and optimized architectures designed for long-term performance and growth.
Read Also: How Healthcare Startups in the USA Leverage Generative AI to Cut 40% Costs?
What are the real-world clinical use cases for AI in healthcare?
Clinical AI supports diagnosis, triage and treatment planning rather than replacing clinical judgment. The established categories are medical imaging analysis, early-warning and deterioration scores, clinical decision support at the point of care, differential diagnosis generation, and patient risk stratification for population health.
SoluLab’s own work in AI in healthcare software development is the clearest illustration. On the GenAI in MedTech platform, the system provides clinical reference question answering, real-time clinical insights, a differential diagnosis generator and clinical documentation generation, with everything sitting behind a HIPAA-compliant security framework and integrated into the EHR through HL7 and FHIR. Measured outcomes on that build: 35% reduction in diagnostic errors, 40% faster clinical decision-making, 25% improvement in treatment accuracy, 30% reduction in patient wait times, 50% increase in clinician efficiency and 60% faster documentation drafting.
The important design point is that the differential diagnosis generator generates. It does not decide. A clinician reviews, and the record shows who decided what. That distinction is not a nicety, it is what keeps a clinical decision support tool outside the heaviest regulatory classifications in most jurisdictions, and it is what clinicians will actually accept. Whether we are building an AI platform and solutions for healthcare providers or a single tool, the software proposes and a named person decides.
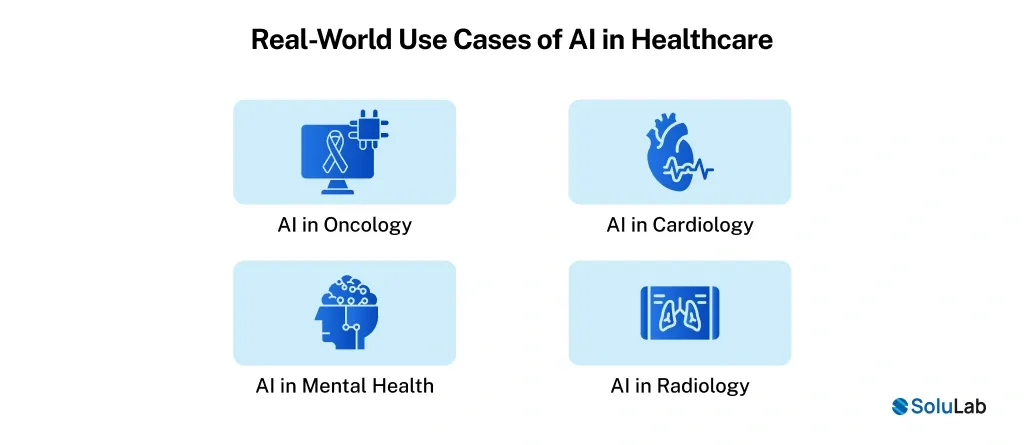
Artificial intelligence is moving beyond pilot projects to the mainstream of the healthcare infrastructure and is providing quantifiable benefits to diagnoses, treatment planning, and patient outcomes in a variety of medical specialties.
1. AI in Oncology
Artificial intelligence models are assisting in the earlier detection of cancers and precision in the treatment. In research published in Nature, AI systems were as capable as radiologists in detecting breast cancer, and it lowers false positives and negatives, as well as assisting in quicker, data-driven decision-making in oncology.
2. AI in Cardiology
AI-based imaging and ECG analysis can be used in cardiovascular care to enhance the timely identification of heart conditions. Research mentioned in The Lancet found that machine learning-based methods detected cardiac abnormalities with an accuracy rate of more than 85 percent, which helped to implement faster intervention and minimize the risk of mortality.
3. AI in Radiology
The radiologists are now assisted by AI agents in healthcare that identify anomalies in X-rays, CT scans, and MRIs. In a study published by Radiology, it has been found that AI systems are capable of saving up to 30 percent of time on image interpretation and have high diagnostic accuracy.
4. AI in Mental Health
The AI-based tools process the speech pattern, behavior, and online activity to detect the signs of depression, anxiety and AI in drug discovery at early stages. AI has the potential to increase access to mental health screening among underserved groups, as studies cited by the World Health Organization indicate.
What does a HIPAA-compliant healthcare AI architecture look like?
A compliant healthcare AI architecture has five layers: interoperable ingestion through HL7 and FHIR, a de-identification and minimum-necessary boundary, a processing layer where models run inside your control plane, an application layer that always routes to a human signer, and a governance layer that satisfies HIPAA audit controls and HTI-1 source-attribute disclosure. The de-identification boundary is the design decision that determines whether the rest is compliant.
Why each layer exists:
Ingestion connects to the EHR through FHIR APIs and HL7 interfaces rather than screen-scraping or flat-file exports. This is what makes the system maintainable when the EHR upgrades, and it is how SoluLab integrated the MedTech platform.
The PHI boundary is where protected health information is minimised, tokenised or de-identified before anything leaves the trusted zone. If a third-party model endpoint sits outside your boundary, this layer decides whether you have a HIPAA problem. The safest pattern, and the one we default to, is to keep inference inside the covered entity’s own cloud tenancy under a business associate agreement, using services such as Azure Health Data Services or an equivalent AWS configuration. It is the default in all of our AI healthcare solutions development work.
Processing holds retrieval over clinical knowledge, the models themselves, and the validation that catches a confidently wrong output before a human sees it. Retrieval-augmented generation grounded in the organisation’s own approved clinical content is strongly preferable to an ungrounded model, both for accuracy and for the HTI-1 source-attribute disclosure you will owe.
The application layer surfaces drafts and suggestions to clinicians and administrators. Nothing is autonomous. Every output has a named human who accepts or rejects it, and that acceptance is recorded.
Governance holds the audit log, model registry, the 31 Predictive DSI source attributes, bias and performance monitoring, and the access controls HIPAA’s Security Rule requires.
How is AI in healthcare regulated?
AI solutions in healthcare sit under four distinct regimes in most Western markets: HIPAA for privacy and security of protected health information, the ONC HTI-1 rule for algorithm transparency inside certified health IT, FDA oversight where software qualifies as a medical device, and the EU AI Act where you operate in Europe. Most vendor content mentions HIPAA and stops. The others are what actually shape the build.
HIPAA
HIPAA governs how protected health information is used and disclosed. For an AI system the practical consequences are: a business associate agreement with every vendor that touches PHI, the minimum necessary standard applied to what the model actually receives, audit controls that record access, encryption in transit and at rest, and a documented risk analysis.
The question that decides most healthcare AI architectures is simple and often asked too late: does PHI leave the covered entity’s control boundary to reach the model? If yes, you need a BAA with that model provider and a defensible basis for the disclosure. If you de-identify properly before the boundary, the calculus changes. Decide this in week one, because it determines your entire deployment topology.
SoluLab has delivered a HIPAA-compliant clinical platform with this architecture, so this is a description of work done rather than a capability claim. [VERIFY: delivery team to confirm current HIPAA attestation and BAA posture before publishing, per the playbook instruction that compliance claims are stated only where SoluLab can support them.]
ONC HTI-1 and algorithm transparency
This is the requirement most healthcare AI pages miss entirely. The HTI-1 final rule, published by ONC in December 2023, adopted a new Decision Support Interventions certification criterion at 170.315(b)(11), the first substantial revision to certified clinical decision support requirements since 2012.
It requires certified health IT to expose 31 source attributes for every Predictive DSI it supplies (and 13 for evidence-based DSIs). Those attributes span the details and output of the intervention, its purpose and intended users, cautioned out-of-scope uses and known limitations, development details and input features, the process used to ensure fairness in development, and the external validation process. Developers must also keep that information current and implement risk management practices covering risk analysis, risk mitigation and governance.
The stated goal is that healthcare organisations can determine whether their Predictive DSIs are fair, appropriate, valid, effective and safe, abbreviated by ONC as FAVES.
For a provider, the practical reading is this. If you are buying or building predictive decision support that lives inside certified health IT, you should be asking for those 31 attributes as a procurement document. If a vendor selling artificial intelligence healthcare solutions cannot produce them, that is a meaningful answer about the product.
FDA and Software as a Medical Device
Where software is intended to diagnose, treat, cure, mitigate or prevent disease, it may meet the definition of a medical device and fall under FDA oversight, with analogous regimes elsewhere such as UKCA and EU MDR. Clinical decision support that merely informs a clinician, where the clinician can independently review the basis of the recommendation, is treated differently from software that directs care. This is a line to walk with regulatory counsel rather than with a vendor, and it should be walked before the build, not after.
EU AI Act
The EU AI Act entered into force on 1 August 2024 and became applicable on 2 August 2026. Annex III high-risk obligations apply from 2 December 2027, and AI embedded in regulated products under Annex I, which is the route most medical device software takes, applies from 2 August 2028. If you place a product on the European market, those are the planning dates.
What Are the 2026 Future Trends of AI in Healthcare?
In 2026, AI healthcare solutions will be in a decisive stage and no longer pilot experiments but a visible impact, increased governance, scalability, and actual clinical collaboration between humans and intelligent technologies.
1. ROI Proof Over Promise
The healthcare leaders are no longer seeking hype, but results. Grand View Research estimates the global AI healthcare market to reach more than $180 billion by 2030, and grow by more than 35 percent each year. Hospitals are focusing on cutting costs, accelerating diagnostics, and efficiency of operations, and will increase AI budgets only afterward.
2. Organizational Readiness
It has been providing AI-ready infrastructure, data modernization, and migration to the cloud. According to McKinsey, more than 60 percent of healthcare executives intend to invest more in AI in the next three years, with the areas of concern being integration, workforce training, and interoperability.
3. Artificial Intelligence-Human Cooperation Is Forming.
Generative AI in US Healthcare startups is reinforcing a critical shift—AI is enhancing clinicians, not replacing them. Research published in The Lancet Digital Health shows AI-supported radiology can improve diagnostic accuracy by up to 20 percent. Administrative burdens are reduced, while clinicians retain control through intelligent decision-support tools.
4. The Staging of AI Agents is Progressively Necessary
The direction of healthcare organisations is towards multi-agent AI systems, which organize the diagnostics, scheduling, documentation, and monitoring of the patient. Gartner estimates that more than half of large businesses will have implemented AI orchestration platforms by the year 2026 to operate complex business processes.
5. The Tech with AI Governance
As the regulation increases, the governance structures become harder. The World Health Organization has also given directives on how AI is used ethically in the medical field, whereas regulatory authorities are enhancing the privacy requirements. Audit trails and transparent algorithms are becoming compulsory.
Read Also: AI Healthcare in the UAE
How SoluLab Helps Companies Build AI in Healthcare Solutions?
SoluLab is an AI-native company that leverages AI within its own workflows to deliver healthcare solutions faster, reduce development costs, and help organizations build scalable, efficient, and compliant AI systems.
With AI driven development approach, here are the AI in healthcare services we provide:
- AI Healthcare Platform Development
- Healthcare Data Analytics & Predictive Modeling
- Generative AI for Healthcare Applications
- AI Agent Development for Healthcare Workflow
- EHR & Healthcare System Integration
- HIPAA-Compliant AI Solutions
- Telemedicine & Remote Monitoring AI Systems
- AI Consulting & Strategy for Healthcare
For example, MedTech partnered with a SoluLab team to build a clinical decision support platform that analyzes fragmented patient data integrated with EHR systems.
The solution delivers accurate diagnostics, guideline-based treatment recommendations, and automated clinical documentation, helping clinicians reduce errors and improve patient outcomes.
Book a free consultation call today to get similar results for your business.

Where does AI actually save money in healthcare today?
The clearest financial case for AI in healthcare is administrative, not clinical. Past analyses put administrative complexity at roughly 10% of US national healthcare expenditure, about $400 billion. The 2023 CAQH Index found $89 billion of that is spent conducting the administrative transactions it tracks, and that the industry could save $18.3 billion by moving the remaining manual and partially electronic transactions to fully electronic processing.
Two things in that data deserve attention.
First, the industry has already proved the mechanism works. CAQH reports that medical and dental providers avoid $193 billion annually through the automation already in place. The argument is not whether automation pays. It is that a large, specific, measured remainder is still manual.
Second, CAQH identified staffing churn as driving more than 75% of the rise in total administrative spend, because less experienced staff take longer to complete the same tasks. That is precisely the problem a well-built AI system addresses. It does not get tired, it does not leave, and it does not need to relearn the prior authorisation rules every time the team turns over.
| Where the burden sits | What AI does about it | Typical measure |
| Clinical documentation | Ambient capture and draft note generation | Minutes per encounter, after-hours charting time |
| Medical coding | Code suggestion from the note, compliance checking | Coder throughput, denial rate, DNFB days |
| Prior authorisation | Assembles the packet, checks payer criteria | Turnaround time, approval rate on first submission |
| Claims and denials | Classifies denial reasons, drafts appeals | Denial overturn rate, days in AR |
| Referrals and correspondence | Drafts letters, extracts referral data | Referral leakage, turnaround |
| Patient communication | Drafts portal replies for clinician approval | Inbox time per clinician |
| Scheduling and capacity | Predicts no-shows, optimises slots and theatre lists | Utilisation, no-show rate |
| Record retrieval and summarisation | Summarises a long chart before an appointment | Pre-visit prep time |
How are clinicians actually using AI in 2026?
Clinician adoption of AI is now mainstream rather than experimental. The AMA’s 2026 Physician Survey on Augmented Intelligence, published 12 March 2026 and covering nearly 1,700 physicians, found that 81% use AI professionally, more than double the 2023 figure. Confidence rose alongside it: over three quarters believe AI improves their ability to care for patients, up from 65% in 2023.
What they actually use it for matters more than the headline.
| Use | Share of physicians |
| Summarising medical research and standards of care | 39% |
| Creating discharge instructions, care plans or progress notes | 30% |
| Documenting billing codes, medical charts or visit notes | 28% |
| Generating chart summaries | 28% |
| Drafting patient portal responses | 19% |
| Translation services | 18% |
| Assistive diagnosis | 17% |
Every one of the top four is a documentation or synthesis task. None of them is a diagnosis. Any healthcare AI roadmap that leads with autonomous clinical decision-making is arguing with the behaviour of the people who would have to use it.
The governance signal in the same survey is just as clear. 70% of physicians see AI as a tool to automate the tasks that contribute to burnout, and 85% want to be consulted or directly involved in decisions about AI adoption. Projects that skip clinician involvement do not fail on technical grounds. They fail on adoption.
One honest counterweight worth repeating, because vendors rarely do: 88% of physicians in that survey reported concern about skill loss among medical students and residents. That is a real, unresolved objection, and the sensible response at an organisational level is to keep AI in the drafting and summarising role rather than the deciding role, which is where the measured value sits anyway.
What are the clinical use cases for AI in healthcare?
Clinical AI supports diagnosis, triage and treatment planning rather than replacing clinical judgment. The established categories are medical imaging analysis, early-warning and deterioration scores, clinical decision support at the point of care, differential diagnosis generation, and patient risk stratification for population health.
SoluLab’s own clinical work is the clearest illustration. On the GenAI in MedTech platform, the system provides clinical reference question answering, real-time clinical insights, a differential diagnosis generator and clinical documentation generation, with everything sitting behind a HIPAA-compliant security framework and integrated into the EHR through HL7 and FHIR. Measured outcomes on that build: 35% reduction in diagnostic errors, 40% faster clinical decision-making, 25% improvement in treatment accuracy, 30% reduction in patient wait times, 50% increase in clinician efficiency and 60% faster documentation drafting.
The important design point is that the differential diagnosis generator generates. It does not decide. A clinician reviews, and the record shows who decided what. That distinction is not a nicety, it is what keeps a clinical decision support tool outside the heaviest regulatory classifications in most jurisdictions, and it is what clinicians will actually accept.
Related SoluLab pages cover the specific clinical technologies in depth, and this page deliberately does not compete with them:
- AI agents in healthcare for agentic clinical and administrative workflows
- Chatbots in the healthcare industry for patient-facing conversational systems
- How generative AI is changing healthcare for GenAI-specific applications
- Machine learning use cases in healthcare for predictive modelling
- Healthcare software development for full platform engineering
What does a HIPAA-compliant healthcare AI architecture look like?
A compliant healthcare AI architecture has five layers: interoperable ingestion through HL7 and FHIR, a de-identification and minimum-necessary boundary, a processing layer where models run inside your control plane, an application layer that always routes to a human signer, and a governance layer that satisfies HIPAA audit controls and HTI-1 source-attribute disclosure. The de-identification boundary is the design decision that determines whether the rest is compliant.
Why each layer exists:
- Ingestion connects to the EHR through FHIR APIs and HL7 interfaces rather than screen-scraping or flat-file exports. This is what makes the system maintainable when the EHR upgrades, and it is how SoluLab integrated the MedTech platform.
- The PHI boundary is where protected health information is minimised, tokenised or de-identified before anything leaves the trusted zone. If a third-party model endpoint sits outside your boundary, this layer decides whether you have a HIPAA problem. The safest pattern, and the one we default to, is to keep inference inside the covered entity’s own cloud tenancy under a business associate agreement, using services such as Azure Health Data Services or an equivalent AWS configuration.
- Processing holds retrieval over clinical knowledge, the models themselves, and the validation that catches a confidently wrong output before a human sees it. Retrieval-augmented generation grounded in the organisation’s own approved clinical content is strongly preferable to an ungrounded model, both for accuracy and for the HTI-1 source-attribute disclosure you will owe.
- The application layer surfaces drafts and suggestions to clinicians and administrators. Nothing is autonomous. Every output has a named human who accepts or rejects it, and that acceptance is recorded.
- Governance holds the audit log, model registry, the 31 Predictive DSI source attributes, bias and performance monitoring, and the access controls HIPAA’s Security Rule requires.
Production stack on the MedTech build: Python, R and JavaScript; TensorFlow, PyTorch and Hugging Face Transformers; Apache Spark, Pandas and NumPy for data processing; PostgreSQL and MongoDB; AWS alongside Azure Health Data Services; HL7 and FHIR APIs for integration; HIPAA, GDPR and OAuth 2.0 for security and compliance; React.js and D3.js for the clinician dashboard; Node.js and Express on the backend.
How much does AI in healthcare cost, and how long does it take?
AI in healthcare builds with SoluLab start at $18,000 for an application that does not need enterprise grading, $24,000 for an MVP built on the enterprise track, and $60,000 and up for a full enterprise-grade platform. A white-label build is $30,000. On timing, a scoped administrative use case integrated through FHIR typically runs 10 to 16 weeks, while clinical work needing validation evidence and governance sign-off runs 6 to 12 months, because the approval path is the long pole rather than the engineering.
| Engagement tier | Price | What it covers |
| Basic | $18,000 | A working application that does not require enterprise grading. Suits a contained administrative or operational task with no PHI crossing a boundary and no clinical decision attached. |
| MVP | $24,000 | A first production version on the enterprise track, with the EHR integration, PHI boundary and audit logging in place from the start. |
| White label | $30,000 | A pre-built platform configured and branded for your organisation, faster to deploy than custom. |
| Advance | $60,000+ | Full enterprise-grade platform: multi-department or multi-site, deep EHR integration, validation evidence, and the HTI-1 source attribute and HIPAA audit machinery described above. |
Healthcare sits in SoluLab’s highest industry pricing band alongside banking, fintech and insurance, and the regulatory section explains why. Anything that becomes a Predictive decision support intervention inside certified health IT carries 31 source attributes to produce and maintain, plus risk analysis, mitigation and governance practices. That is sustained engineering, not a launch document.
Budget for running costs separately. Model usage or GPU hosting, monitoring, retraining and periodic revalidation recur monthly and are not in the build price.
What moves you between tiers:
| Cost driver | Cheaper | More expensive |
| EHR integration | Modern EHR with a working FHIR API | Legacy interfaces, custom HL7 feeds, vendor gatekeeping |
| PHI handling | De-identified data, inference inside your tenancy | PHI crossing a boundary, BAAs, data residency constraints |
| Validation burden | Administrative task, clinician reviews output | Clinical decision support needing external validation evidence |
| Governance | Internal tool, no DSI certification exposure | Predictive DSI inside certified health IT, 31 source attributes to produce and maintain |
| Data readiness | Structured, coded, reasonably complete records | Scanned documents, free text, fragmented across systems |
| Change management | One department, willing champions | Multi-site rollout, clinician scepticism, union or works council involvement |
Two patterns repeat. The EHR vendor relationship is frequently the critical path, because integration access depends on their timetable rather than yours, so open that conversation in week one. And change management is routinely underfunded. The AMA data showing 85% of physicians want involvement in AI adoption decisions is not a soft finding, it is a delivery risk with a number attached.
How should a healthcare organisation implement AI?
- Pick an administrative or operational use case with a measurable baseline. Not “AI for the hospital”. Something like “reduce after-hours charting time per clinician from 72 to 40 minutes a week”. If you cannot state the current number, measuring it is step one.
- Draw the PHI boundary before you draw anything else. Decide what data the model sees, where inference runs, and which vendors need a BAA. This single decision constrains every later choice.
- Open the EHR integration conversation immediately. FHIR API access, test environments and vendor timelines are external dependencies. They do not compress because your project plan says so.
- Involve clinicians from the first week, not at rollout. 85% of physicians want a say in AI adoption. Give it to them, and give them the ability to reject outputs and have that rejection recorded.
- Build the governance artefacts alongside the build. Model registry, audit logging, the HTI-1 source attributes if you are inside certified health IT, bias and performance monitoring. Retrofitting these into a live clinical system is expensive and sometimes impossible.
- Run in shadow mode, then expand by department. Compare the system’s outputs against human decisions on real cases before anything touches a patient workflow. Expand one department at a time, with each department’s champion visible to the next.
Why do healthcare AI projects stall?
Most AI in healthcare programmes stall for the same five reasons.
The PHI question arrives too late. The pilot runs on an ungoverned endpoint, works well, and then compliance review establishes it cannot go to production in that form. The rebuild is effectively a new project.
EHR integration is assumed rather than confirmed. Teams plan twelve weeks on the assumption that FHIR access is available, and discover the vendor’s queue is longer than the project.
Clinicians were not consulted. The system is technically sound and nobody uses it. This is the most common failure, and the cheapest to avoid.
The documentation is messier than the pilot data. Scanned faxes, handwritten notes, free text that does not follow any template. If your pilot ran on clean structured records, it proved very little about production.
Scope started clinical. The organisation picked the most regulated, highest-stakes use case because it had the biggest headline, then spent nine months in validation and governance while the administrative wins that would have funded the programme went unbuilt.
And one honest limitation: AI does not fix a process that is broken for structural reasons. If prior authorisation is slow because a payer takes eleven days to respond, automating your side of the packet helps your staff and does not change the eleven days. Be precise about which part of the delay you actually own.
Conclusion
Artificial intelligence is no longer an experiment but a necessity in healthcare. The future is not a series of single AI applications, but a collection of integrated, secure, and scalable systems to enhance clinical care, cut spending, and increase access to care.
The difference: Predictive diagnostics to AI-assisted processes and patient monitoring in real-time have an impact that is quantifiable and functional.
But the success in the long run is determined by governance, interoperability, workforce preparedness, and distinct ROI. The strategic investments of healthcare organizations today will help transform the model of care to an elevated, data-driven, and patient-centered care in the coming decade.
SoluLab, an AI development company, can help you build AI platforms or integrate them into existing systems for smoother workflows. Book a free discovery call today!
FAQs
Neha is a curious content writer with a knack for breaking down complex technologies into meaningful, reader-friendly insights. With experience in blockchain, digital assets, and enterprise tech, she focuses on creating content that informs, connects, and supports strategic decision-making.


